
NMN Evidence Card: 25 Human Studies, Their Results, Funding and Registry Gaps
NMN evidence card: 25 human studies checked one by one for between-group results, funding and registration; 11 trials with no article; EU, US and UK status.
NMN evidence card: 25 human studies checked one by one for between-group results, funding and registration; 11 trials with no article; EU, US and UK status.
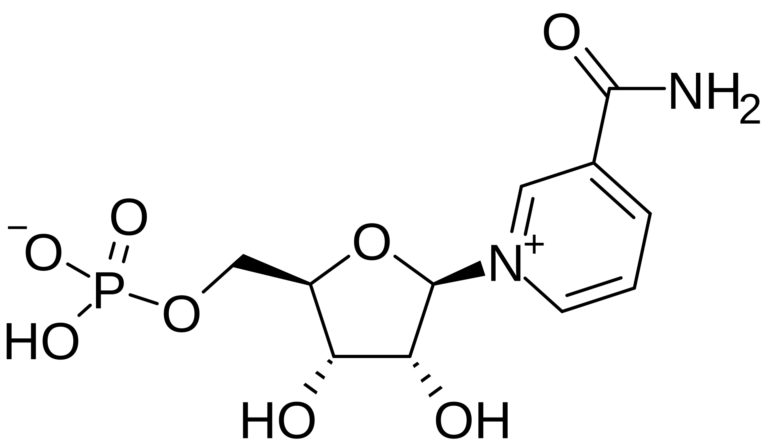
β-Nicotinamide mononucleotide (NMN) sits one enzymatic step upstream of NAD+, the coenzyme that falls with age in several rodent tissues. That position made it the most marketed NAD+ precursor of the past decade. This dossier is built on a hand-curated layer: all 25 human intervention studies, read one by one (21 in full text), with their between-group results, attrition, funding, conflict statements and registrations, and every NMN trial registered on ClinicalTrials.gov. A rule-based census of 2,545 PubMed records provides context, with its uncertainty stated. It describes literature and regulation; it gives no basis for any use.
NMN Evidence Card · version 1.0-rc · data cut-off 2026-10-17 · Condor Research Editorial · Methods · How to cite
Declaration of interest: Condor Research sells NMN as a research-use-only reference material. This dossier was written and funded by Condor Research. All counts can be reproduced from the published dataset and scripts.
| Layer | Field | Value (2026-10-17) | How it was obtained |
|---|---|---|---|
| Human (curated) | Human intervention studies, primary reports | 25 (894 participants; median 30; longest 24 weeks) | targeted search, each study read by hand |
| Human (curated) | With a control group / with a designated primary / CI published for the primary between-group difference | 19 / 16 / 1 | abstracts and 21 full texts; definition in the effects section |
| Human (curated) | Funded by, or with declared ties to, NMN-related companies | 20 of 25 (12 directly funded) | funding and conflict sections |
| Registry (curated) | Finished ClinicalTrials.gov registrations with no PubMed article located | 11 of 17 | matched one by one |
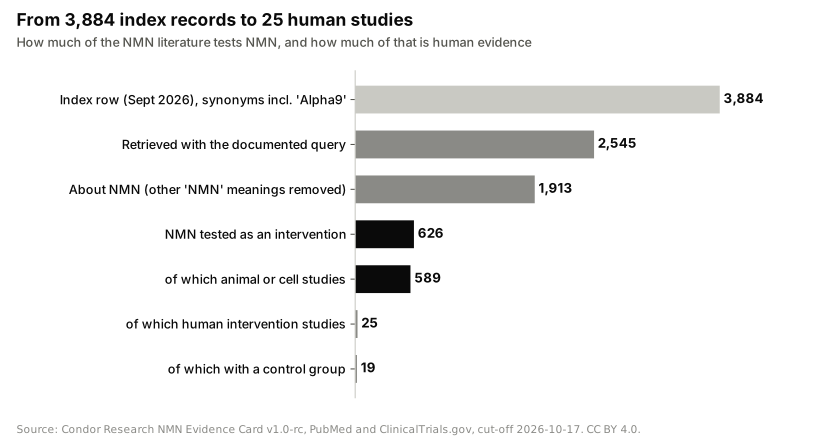
| Census (context) | PubMed records about NMN / in which NMN is given | 1,913 / 626 (of 2,545 retrieved) | rules plus hand review; blind second coder: κ 0.65 at first pass (see Methods) |
| Census (context) | Previous Evidence Index row | 3,884 records, 0 trials | inflated by ambiguous synonyms and a query error |
The curated rows are the evidence; registration and full-text status for each study are in the effects table; the census rows are context and carry classification error (agreement with a blind second coder on “NMN given versus not”: 88.2%, κ 0.65, before rule revision). The September index row counted the supplier synonym “Alpha9” (951 records on unrelated α9 proteins) and every use of the abbreviation “NMN”, which also stands for normetanephrine and N-methylnicotinamide. Its trial count was zero because of a query-syntax error, since corrected in the index code.
Evidence level in one line: a large preclinical literature; 25 short human studies (median 30 participants, longest 24 weeks) that mostly show a rise in blood NAD+ and have not shown consistent clinical effects in controlled comparisons.
Key findings
- 25 human intervention studies (894 participants, median 30, none longer than 24 weeks) make up the whole human literature on NMN to October 2026.
- Blood NAD+ rose in 15 of the 17 studies that measured it. That is the only replicated human finding.
- Clinical effects are not established. Of 16 controlled studies with a designated primary endpoint, one publishes a confidence interval for the between-group difference on it.
- 20 of 25 studies were funded by, or had declared ties to, NMN-related companies; two conflict statements contradict their own funding sections.
- 11 of 17 finished ClinicalTrials.gov registrations had no PubMed article at the cut-off, including a 56-participant follow-up whose posted results do not favour NMN.
- The EU authorisation of one applicant’s β-NMN passed committee on 24 September 2026; FDA no longer excludes NMN from the supplement definition.
What this dossier adds to existing reviews
- The 2026 systematic review with GRADE pooled 15 randomised trials for safety and metabolic outcomes.1 It did not tabulate funding, conflict statements or registry correspondence; this dossier does, for all 25 human studies including uncontrolled ones.
- No review we found compares completed NMN registrations with published articles. Here: 17 finished registrations, 11 without a PubMed article, and the posted results of the largest unpublished one.
- Reviews cite “NMN research” counts without disambiguation. Here: 632 of 2,545 PubMed hits for the query use “NMN” for something else, and a second coder checked the classification blind.
- Regulatory status is current to the European Standing Committee vote of 24 September 2026 and the FDA letter of 29 September 2025, from primary documents.
What does the NMN literature actually contain?
Before counting, we resolved the compound in PubChem (CID 14180) and checked every synonym against PubMed. Two synonyms that automated indexes pick up are traps. “Alpha9” is a supplier trade name that returns 951 papers on unrelated α9 proteins. “NMN” is also the standard abbreviation for normetanephrine, a catecholamine metabolite used in phaeochromocytoma diagnostics, and for N-methylnicotinamide, a probe of renal transporters. The documented query (see Methods) retrieved 2,545 records; 632 of them (25%) use “NMN” for something else, 245 in the catecholamine family alone.
The 1,913 records about nicotinamide mononucleotide fall into four groups. The unit in this section is the PubMed record, not the study, and the counts are approximate: a blind second coder agreed with the first-pass rules on 88.2% of records for “NMN given versus not” (κ 0.65). Treat them as orders of magnitude, not as precise figures.
| Group | Records | Share of NMN records |
|---|---|---|
| NAD+ pathway biology: NMN as metabolite, substrate or enzyme product (NMNAT, NAMPT, CD38, SARM1) | 689 | 36% |
| NMN given as a tested agent, including as a rescue or comparator arm (cells, animals, humans) | 626 | 33% |
| Chemistry, analytical methods, biosynthesis and production | 367 | 19% |
| Reviews, systematic reviews, meta-analyses, conference reports and regulatory opinions | 217 | 11% |
| Comments, errata | 14 | 1% |
Classification of 1,913 PubMed records by the role NMN plays in each. Rule-based classification on title, abstract, MeSH and publication type, with 125 records reviewed and corrected by hand; blind double coding of a 15% random sample is reported in Methods. Source: Condor Research census, query date 2026-10-17.
How fast has the intervention literature grown, and who writes it?
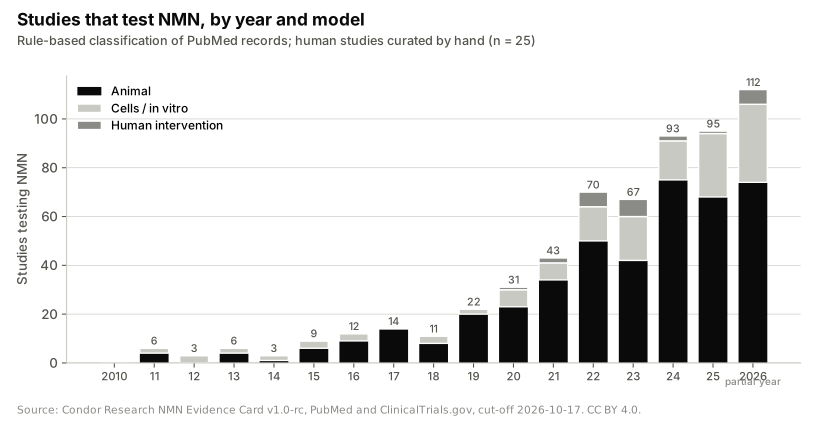
Of the 626 records in which NMN is given, 522 (83%) were published from 2020 onwards. Chinese first authors sign 345 (55%), US 90 (14%) and Japanese 65 (10%). The two laboratories most associated with the molecule’s public profile, Shin-ichiro Imai’s at Washington University and David Sinclair’s at Harvard, appear as authors on 28 (4.5%). Authorship is therefore spread across many groups. That is a statement about authorship, not about replication: we did not test whether individual preclinical findings were reproduced, and many of these papers test different outcomes in different models.
The census contains no peer-reviewed lifespan study of NMN in normally ageing mammals. A 2024 preprint from the Sinclair group reports an 8.5% increase in median lifespan in female mice and none in males.2 A 2026 report on a different compound included NMN as a comparator arm and found no significant difference in median lifespan versus placebo in adult mice.3 The best-known long-term mouse study, a 12-month administration from the Imai group, measured physiological decline rather than survival.4
What have the 25 human studies tested?
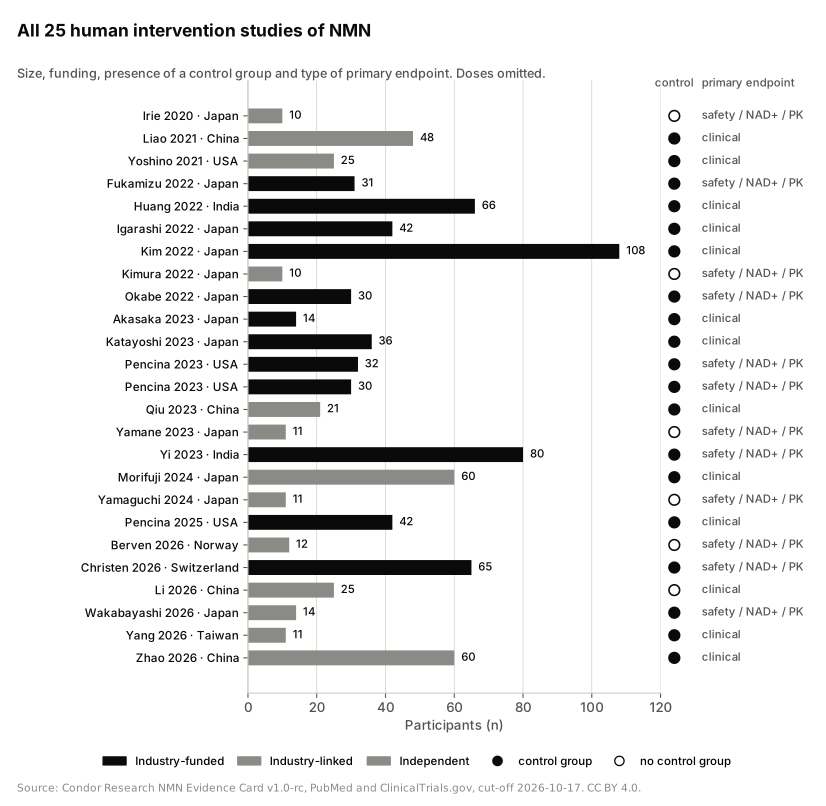
We identified 25 primary reports of human intervention studies with NMN as the test agent, published from 2020 to 2026. Excluded: protocols, post hoc reanalyses of trials already counted, multi-ingredient formulas and an uncontrolled sub-study inside a mouse paper. Doses, routes, timing and schedules are omitted on purpose.
| Study | Country | Design | n | Duration | Primary endpoint | Blood NAD+ | Funding |
|---|---|---|---|---|---|---|---|
| Irie 20205 | Japan | single-arm, non-randomised | 10 | single administration, 5 h follow-up | safety and pharmacokinetics | metabolites only | Industry-linked |
| Liao 20216 | China | RCT, double-blind, placebo, 4 arms | 48 | 6 weeks | aerobic capacity (CPET); no single primary designated | not reported | Industry-linked |
| Yoshino 20217 | USA | RCT, double-blind, placebo | 25 | 10 weeks | muscle insulin sensitivity (clamp) | increased (PBMC) | Industry-linked |
| Fukamizu 20228 | Japan | RCT, double-blind, placebo | 31 | 4 weeks | safety (haematology, biochemistry, urine, body composition, adverse events) | not measured | Industry-funded |
| Huang 20229 | India (sponsor China) | RCT, double-blind, placebo | 66 | 60 days | co-primaries: serum NAD+/NADH, 6-min walk, blood pressure, SF-36 | increased (serum NAD+/NADH) | Industry-funded |
| Igarashi 202210 | Japan | RCT, double-blind, placebo | 42 | 6 or 12 weeks | blood NAD+ and skeletal muscle index | increased (whole blood) | Industry-funded |
| Kim 202211 | Japan | RCT, double-blind, placebo, 4 groups | 108 | 12 weeks | sleep quality and fatigue | not measured | Industry-funded |
| Kimura 202212 | Japan | single-arm | 10 | single session | safety | increased | Industry-linked |
| Okabe 202213 | Japan | RCT, double-blind, placebo | 30 | 12 weeks | safety | increased (whole blood) | Industry-funded |
| Akasaka 202314 | Japan | RCT, double-blind, placebo | 14 | 24 weeks | safety; grip strength and walking speed | not reported in abstract | Industry-funded |
| Katayoshi 202315 | Japan | RCT, double-blind, placebo | 36 | 12 weeks | NAD+ metabolites and arterial stiffness (no single primary designated) | serum NAD+ below quantification limit; nicotinamide increased | Industry-funded |
| Pencina 202316 | USA | RCT, double-blind, placebo, 3 arms | 32 | 14 days | pharmacokinetics/pharmacodynamics (blood NMN, NAD+) | increased | Industry-funded |
| Pencina 202317 | USA | RCT, single-centre, double-blind, placebo, 2:1 | 30 | 28 days | none designated; sample size set for safety and rise in blood NAD+ and its metabolites | increased | Industry-funded |
| Qiu 202318 | China | randomised, open-label, NMN vs lifestyle modification (no placebo) | 21 | 6 weeks | flow-mediated dilation and baPWV | increased (PBMC) | Independent |
| Yamane 202319 | Japan | single-arm | 11 | 12 weeks | plasma NMN and NAD+ (stated aim; no primary designated) | increased (plasma) | Industry-linked |
| Yi 202320 | India (sponsor USA/China) | RCT, double-blind, placebo, 4 arms | 80 | 60 days | blood NAD+ | increased | Industry-funded |
| Morifuji 202421 | Japan | RCT, double-blind, placebo | 60 | 12 weeks | stepping test | increased | Industry-linked |
| Yamaguchi 202422 | Japan | single-arm, open-label | 11 | 8 weeks | safety | increased (PBMC) | Industry-linked |
| Pencina 202523 | USA | RCT, placebo, 3:2 | 42 | 14 days | change in serum creatinine | increased | Industry-funded |
| Berven 202624 | Norway | open-label phase 1 pharmacokinetics (NR or NMN) | 12 | several weeks | blood and cerebral NAD | increased | Independent |
| Christen 202625 | Switzerland | randomised, open-label, placebo, 4 arms (NR, NMN, nicotinamide, placebo) | 65 | 14 days | whole-blood NAD+ | increased | Industry-funded |
| Li 202626 | China | single-arm, open-label, phase 1/2 | 25 | 2 weeks | safety/tolerability and platelet response | not reported in abstract | Independent |
| Wakabayashi 202627 | Japan | randomised crossover, two administration formats | 14 | single administrations | blood NMN (between-format difference) | measured, no between-format difference | Industry-linked |
| Yang 202628 | Taiwan | randomised crossover, placebo | 11 | 7 days per period | muscle cell infiltration and mitochondrial number after BFR exercise | not measured | Independent |
| Zhao 202629 | China | RCT, double-blind, placebo, 4 arms (PQQ, NMN, both, placebo) | 60 | single session | interoception after exhaustive exercise | not measured | Independent |
All human intervention studies of NMN indexed in PubMed to 2026-10-17. Funding: industry-funded = financed or sponsored by a company; industry-linked = product donated by a manufacturer, company employees among the authors, or investigator patents or funding from a manufacturer; independent = none declared. Dataset: dataset.json.
What did the controlled comparisons show on their primary endpoints?
Nineteen of the 25 studies compared NMN with a control. We define the primary comparison as the between-group difference (NMN minus control) on the endpoint the authors or the registry designate as primary; with co-primaries, any one of them. A confidence interval counts only if the paper publishes an estimate of that difference with its interval. Within-group intervals, group means with intervals, interaction tests without an estimate and intervals for secondary outcomes do not count. Three controlled studies designate no primary endpoint and are treated as not applicable. The table gives, for each study, the reported result on the primary endpoint, whether a confidence interval for the primary comparison is published, attrition, a simplified risk-of-bias judgement and whether the reported primary matches the registered one. We do not summarise these results as a success rate: the endpoints, populations and durations are too different for a count of “positive” trials to mean anything.
| Study | Primary endpoint | Between-group result as reported | CI published | Randomised / analysed | Risk of bias (simplified) | Registered vs reported primary |
|---|---|---|---|---|---|---|
| Liao 20216 | aerobic capacity (CPET); no single primary designated | ventilatory-threshold measures higher than control in two of three NMN arms (Cohen's d with 95% CI in paper); VO2max, O2-pulse and peak power not different | n/a: no single designated primary (between-group effect sizes with CIs reported for ventilatory-threshold measures) | 48 randomised; analysed n not stated in abstract | some concerns: no single primary designated; many arm-by-arm comparisons | ChiCTR2000035138 not checked |
| Yoshino 20217 | muscle insulin sensitivity (clamp) | significant time × condition × group interaction for insulin-stimulated glucose disposal (P = 0.022), followed by post hoc tests showing an increase with NMN and no change with placebo; no estimate or CI of the NMN-minus-placebo contrast | no | 25 randomised, 25 analysed | some concerns: small; contrast reported as an interaction test without an effect estimate | matches NCT03151239 (muscle insulin sensitivity) |
| Fukamizu 20228 | safety (haematology, biochemistry, urine, body composition, adverse events) | no between-group differences in safety measures | no | 31 randomised | some concerns: small | UMIN000043084 not checked |
| Huang 20229 | co-primaries: serum NAD+/NADH, 6-min walk, blood pressure, SF-36 | serum NAD+/NADH +38% from baseline vs +14.3% with placebo (within-group); HOMA-IR difference not significant | no | 66 randomised, 62 analysed per protocol | high: per-protocol, within-group comparisons, sole author employed by sponsor | matches NCT04228640 co-primaries |
| Igarashi 202210 | blood NAD+ and skeletal muscle index | skeletal muscle index not different from placebo; blood NAD+ higher than placebo; gait speed and left grip nominal only | no | 42 randomised; at week 6 a supplier error gave 11 participants per group the other supplement; week-12 data of these 22 were excluded by ethics-committee decision, leaving 20 (10 per group) at 12 weeks | high: supplier allocation error; 22 of 42 participants' week-12 data excluded, disrupting the randomised balance (acknowledged by the authors) | UMIN000036321 not checked |
| Kim 202211 | sleep quality and fatigue | no significant group-by-time interaction for sleep quality (PSQI); interactions for drowsiness and chair-stand, with improvement also in a placebo group | no | 108 randomised; analysed n not stated in abstract | some concerns: four-group design with many outcomes; registry record not checked | UMIN000038097 (cited in Methods) not checked |
| Okabe 202213 | safety | no between-group differences in safety measures; whole-blood NAD+ higher than placebo | no | 30 randomised (15/15) | low to some concerns: small; registered | matches jRCTs041200034 (safety) |
| Akasaka 202314 | safety; grip strength and walking speed | grip strength change +1.25 kg (95% CI -2.31 to 4.81) vs -0.44 (-4.15 to 3.26); walking speed +0.033 vs +0.014 m/s; no difference | no between-group CI in abstract (within-group CIs only); full text not read | 14 analysed | high: very small; no registration cited | no registration located |
| Katayoshi 202315 | NAD+ metabolites and arterial stiffness (no single primary designated) | serum nicotinamide higher than placebo (p=0.037); serum NAD+ below quantification limit; baPWV not different (p=0.097) | n/a: no designated primary | 36 randomised; analysed n not stated in abstract | some concerns: primary not designated | UMIN000045205 not checked |
| Pencina 202316 | pharmacokinetics/pharmacodynamics (blood NMN, NAD+) | rise in blood NMN and NAD+ vs placebo | not reported in abstract; full text not read | 32 randomised | some concerns: no registration cited | no registration located |
| Pencina 202317 | none designated; sample size set for safety and rise in blood NAD+ and its metabolites | blood NAD+ rose with NMN and not with placebo (reported graphically, no between-group estimate in text). Secondary: body weight -1.9 kg (95% CI -3.3 to -0.5), diastolic blood pressure -7.0 mmHg (-13.4 to -0.6), total and LDL cholesterol lower; authors state all P values are nominal; strength, aerobic capacity, insulin sensitivity and liver fat not different | n/a: no designated primary (CIs reported for secondary outcomes) | 30 randomised (21 NMN, 9 placebo); 2 did not complete; all randomised analysed | some concerns: no designated primary; nominal P values across many outcomes; sponsor employees among co-authors | no registration cited in the full text |
| Qiu 202318 | flow-mediated dilation and baPWV | FMD and baPWV changes differed significantly in favour of NMN vs lifestyle advice | no | 21 randomised, 19 analysed | high: open-label, no placebo, small | matches NCT04903210 (FMD, baPWV) |
| Yi 202320 | blood NAD+ | blood NAD+ higher than placebo in all NMN arms (p<=0.001) | no | 80 randomised, 80 analysed | some concerns: per-protocol; sponsor-run | partial: registry lists NAD+, 6-min walk, SF-36 and a telomerase part as primaries; paper reports NAD+ as sole primary and no telomerase results |
| Morifuji 202421 | stepping test | stepping test not different from placebo at 4 or 12 weeks; 4-m walking time and blood NAD+ (secondary) favoured NMN | not reported in abstract; full text not read | 60 randomised | some concerns | matches UMIN000047871 per paper |
| Pencina 202523 | change in serum creatinine | serum creatinine change not different from placebo; cystatin C, inflammation and severity also not different | no (group means with 95% CIs in figures; no contrast estimate) | 42 randomised (3:2) | some concerns | mismatch: registry primary is serum cystatin C; paper designates serum creatinine (both not different) |
| Christen 202625 | whole-blood NAD+ | whole-blood NAD+ vs placebo +43.1 µM (95% CI 32.7 to 53.4) for NMN | yes | 67 randomised (15 to NMN) | some concerns: open-label; objective laboratory endpoint | matches NCT05517122 (whole-blood NAD+) |
| Wakabayashi 202627 | blood NMN (between-format difference) | no difference in blood NMN, nicotinamide or NAD+ between the two formats; terminal catabolites higher with one format | no | 14 randomised, 13 completed | some concerns: format comparison, no placebo | UMIN000049530 not checked |
| Yang 202628 | muscle cell infiltration and mitochondrial number after BFR exercise | NMN abolished the 171% exercise-induced rise in muscle mitochondrial content seen with placebo; inflammatory mRNA lower | no | 15 enrolled, 11 analysed | high: 27% withdrawal; no registration cited | no registration located |
| Zhao 202629 | interoception after exhaustive exercise | no group-by-time interaction for the NMN arm on interoception scores | no (group means with CIs; no contrast estimate) | 60 randomised | some concerns | ChiCTR2500112623 not checked |
Controlled human comparisons of NMN. “Risk of bias” is a simplified judgement on the RoB 2 domains (randomisation reported, blinding, attrition, selection of the reported result); it is not a formal RoB 2 assessment. Registry correspondence was checked on ClinicalTrials.gov and jRCT; UMIN and ChiCTR records marked “not checked” were not read.
Three patterns stand out. First, the endpoints that consistently differ from control are NAD+ and its metabolites in blood. Second, of the 16 controlled studies with a designated primary endpoint, 1 publishes a confidence interval for the between-group difference on it; 12 do not (checked in full text), and for 3 assessed from the abstract only none is reported there. Several report within-group change or an interaction test without an effect estimate, which leaves the size of any NMN-versus-control difference unknown. Third, two studies report a primary endpoint different from the registered one: one registered serum cystatin C and reported serum creatinine (neither differed from placebo),23 and one registered NAD+, walking distance, SF-36 and a telomerase sub-study as primaries and reported NAD+ alone as primary, without telomerase results.20 Four studies cite no registration in the paper or abstract we read. One 30-participant MIB-626 study designated no primary endpoint, sized its sample for safety and the rise in blood NAD+, reported that rise only graphically, and states that all its P values, including those for weight, blood pressure and cholesterol, are nominal.17
The one human finding with replication is a rise in blood NAD+. Controlled evidence for clinical effects is sparse, small and rarely reported with intervals.
How does this compare with the 2026 GRADE review?
The most recent systematic review searched six databases to 13 May 2026, included 15 randomised trials and graded certainty with GRADE.1 It found no increase in adverse events or liver enzymes, no effect on body weight, BMI, fasting glucose, HbA1c, lipids or systolic blood pressure, and a small decrease in diastolic blood pressure that its authors call hypothesis-generating. Certainty was moderate for liver enzymes, body weight, BMI, glucose, triglycerides and total adverse events, low for HbA1c, LDL cholesterol and blood pressure, and very low for HOMA-IR and serious adverse events. Our reading of the primary reports agrees with that picture. We add what a pooled analysis does not show: who funded each study, where disclosures conflict with funding sections, which trials match their registrations, and which finished trials are missing from the literature. A 2025 meta-analysis that kept NMN and NR separate found no effect of NMN on skeletal muscle index, grip strength, gait speed or chair-stand time.30
Who paid for the human evidence?
Twelve of the 25 studies were funded or sponsored by a company (48%), and eight more had declared ties to one: product donated by the manufacturer, company employees among the authors, or investigator patents and research funding from NMN suppliers. Five (20%) declared none. Counting only direct funding, the industry share is 48%; counting declared ties as well, 80%. Three manufacturer families recur: Mitsubishi Corporation Life Sciences (four studies), Metro International Biotech (three) and Oriental Yeast, which supplied product for the Keio and Washington University studies.5,7,22
Two disclosures do not match the papers they sit in. One trial declares “no conflict of interest” while its funding section states that Mitsubishi Corporation Life Sciences provided the research funds, the supplements and the publication fee, and three of its authors are company employees.11 Another declares “no competing interests” while every author is affiliated with DHC Corporation, which funded it.15 The 66-participant trial sponsored by Effepharm, whose sole author is an Effepharm employee,9 is the human study that EFSA’s 2026 opinion identifies as the applicant’s own.31
Industry funding does not invalidate a trial. It means that most of the human evidence was produced by parties with a commercial interest in NMN, a category that includes the publisher of this dossier.
Which registered NMN trials have no article in PubMed?
ClinicalTrials.gov lists 37 interventional studies with an NMN arm. Seventeen are completed or terminated. For 11 of them we located no results article in PubMed at the cut-off; two of those 11 have posted results on the registry. Ten of the 11 finished more than 12 months before the cut-off. Industry is the lead sponsor on 13 of the 37 registrations. Absence here means “not located in PubMed by registration number or by matching to published trials on 2026-10-17”; articles may exist elsewhere or appear later.
| Registration | Lead sponsor | Enrolled | Completed | Article in PubMed | Results on registry | Months since completion | Note |
|---|---|---|---|---|---|---|---|
| NCT04862338 | Seneque SA | 17 | 2022-04-04 | none located | no | 54.4 | |
| NCT04817111 | Metro International Biotech, LLC | 7 | 2022-05-19 | none located | yes | 53.0 | results posted on ClinicalTrials.gov 2023-07-17; no peer-reviewed report found |
| NCT05175768 | Vedic Lifesciences Pvt. Ltd. | 69 | 2022-07-16 | none located | no | 51.1 | terminated |
| NCT04910061 | Seneque SA | 24 | 2023-03-01 | none located | no | 43.6 | |
| NCT04664361 | Seneque SA | 131 | 2023-05-30 | none located | no | 40.6 | |
| NCT05305677 | Peking University Third Hospital | 88 | 2024-12-31 | none located | no | 21.5 | |
| NCT04571008 | Washington University School of Medicine | 56 | 2025-03-04 | none located | yes | 19.4 | results posted on ClinicalTrials.gov 2026-03-11; no peer-reviewed report found |
| NCT05882214 | Zhejiang Chinese Medical University | 22 | 2025-04-06 | none located | no | 18.4 | |
| NCT07569627 | University of Taipei | 60 | 2025-05-01 | none located | no | 17.5 | same institution as PMID 41705654 (n=11, BFR exercise); the paper does not cite this registration and the registered design (60 participants, several arms) differs |
| NCT05878119 | Metro International Biotech, LLC | 124 | 2025-08-04 | none located | no | 14.4 | |
| NCT05040321 | Brigham and Women's Hospital | 22 | 2026-04-30 | none located | no | 5.6 |
Completed or terminated interventional NMN studies on ClinicalTrials.gov for which no results article was located in PubMed. Search by registration number and by matching published trials to their registrations; query date 2026-10-17. Sensitivity: excluding registrations completed less than 12 months before the cut-off, 10 of 16; counting results posted on the registry as reported, 9 of 17.
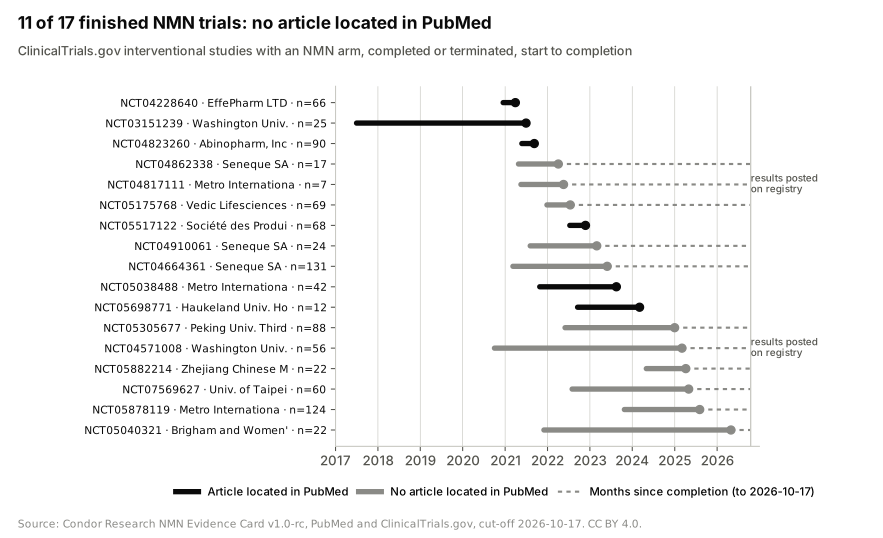
One of the eleven is the larger successor to the most cited human efficacy result. In 2021 the Washington University group reported that muscle insulin sensitivity rose after 10 weeks of NMN in 25 women with prediabetes.7 The same institution registered a randomised, quadruple-masked trial on the same primary endpoint over 16 weeks (NCT04571008, 56 enrolled, 40 analysed). It completed in March 2025 and posted results on 2026-03-11: mean change in muscle insulin sensitivity 13.5 with NMN and 19.0 with placebo (standard deviations 88.4 and 95.0).32 On the posted numbers, NMN did not outperform placebo. No article was located at the cut-off. We draw no conclusion about the direction of results in the other unpublished trials, which posted nothing.
Japanese studies are mostly registered on UMIN-CTR and jRCT. Among those we read, a placebo-controlled hearing trial whose recruitment the registry lists as complete (jRCTs031220373) and a tinnitus trial that is recruiting (jRCTs041220129) have no article in PubMed. Because jRCT and UMIN offer no complete public query interface, we computed no rate for them.
Is NMN evidence the same as NR or “NAD+ precursor” evidence?
No, and much of what is written about NMN borrows from nicotinamide riboside (NR). Only 2 of the 25 NMN studies also tested NR in the same protocol.25,24 Several widely cited meta-analyses pool NMN and NR; kept apart, the NMN-only estimates for muscle outcomes are null.30 In a 65-participant randomised comparison, NMN and NR raised whole-blood NAD+ to a similar extent, and ex vivo work in the same paper attributed much of that effect to gut bacteria converting both precursors to nicotinic acid.25 For the pooled human picture across precursors, see our review of NAD+, NMN and NR human evidence; for the coenzyme itself, NMN versus NAD+.
What does this literature allow, and not allow, us to say?
- Published human studies report higher blood NAD+ after NMN administration. Fifteen of 17 human studies that measured it reported an increase, across five countries and several manufacturers; the 2026 randomised comparison estimates the difference from placebo at 43.1 µM (95% CI 32.7 to 53.4) after 14 days.25
- No clinical effect in humans is established. Controlled studies with clinical primary endpoints are few, small and heterogeneous; the largest unpublished successor of the most cited positive result posted numbers that do not favour NMN; the 2026 GRADE review found no broad metabolic benefit.
- The human evidence base is small and short. 894 participants across 25 studies, median 30 per study, none longer than 24 weeks.
- Most human evidence is industry-produced. 48% directly funded, 80% including declared ties; two studies contain conflict statements that contradict their own funding sections.
- The published record is incomplete. 11 of 17 finished registrations had no PubMed article at the cut-off, a median 21.5 months after completion; two published trials report primaries that differ from their registrations.
- Counts of “NMN research” are unreliable unless the abbreviation is disambiguated. A quarter of PubMed hits for the query are about something else.
What is NMN’s legal status in the EU, the UK, the US and Japan?
The answer has changed more in the last 13 months than in the previous five years, and it depends on what NMN is sold as. As a food or supplement it is regulated food by food, jurisdiction by jurisdiction. A research reference material sits outside food law only as long as it is not presented for consumption. Status below is as of 2026-10-17, from primary sources.
| Jurisdiction | Status | Primary source and date |
|---|---|---|
| European Union: classification | Novel food. No significant consumption in the EU before 15 May 1997 was established; category 3(2)(a)(i) of Regulation (EU) 2015/2283. | Commission consultation on novel-food status, published 2022-10-1133; Regulation (EU) 2015/228334 |
| European Union: safety assessment | EFSA concluded that one applicant’s chemically synthesised β-NMN is safe under the proposed conditions of use in food supplements for adults, excluding pregnant and lactating women, and is a source of bioavailable niacin. Adopted 2026-03-04, published May 2026. | EFSA Journal 2026;24(5):e1000731 |
| European Union: authorisation | The Standing Committee (PAFF, novel food section) gave a positive opinion on 2026-09-24 to a draft implementing regulation adding β-NMN to the Union list. The draft annex names the applicant as EffePharm (Shanghai) Ltd. and sets the end of data protection at five years after entry into force; during that period only the applicant may place it on the EU market unless another applicant obtains its own authorisation. Not published in the Official Journal at the cut-off. | Comitology register D118035/02, draft act and annex35 |
| European Union: other applications | Two NMN procedures have been terminated without updating the Union list (decision of 2022-03-31, C(2022) 1900; NF 2025/35790, C(2026) 6813). Other applications remain pending. | Commission, decisions terminating the procedure36 |
| United Kingdom | Novel food application RP-2116 (Effepharm) “in progress”, risk-assessment phase; record last modified 2026-10-01. No GB authorisation. | FSA register of regulated product applications37 |
| United States | On 2022-10-11 FDA told a notifier that NMN was excluded from the dietary-supplement definition because it had been authorised for investigation as a drug. On 2025-09-29 FDA concluded that NMN “is not excluded” under the race-to-market clause, because it was marketed as a supplement in the US, as early as 2017, before that authorisation. The letter addresses that clause only; it is not an approval of any product and does not decide safety or compliance with other requirements. | FDA response to citizen petition, docket FDA-2023-P-0872, 2025-09-2938 |
| Japan | The MHLW working group on ingredient classification concluded on 2019-09-13 that β-NMN belongs on the list of ingredients not judged to be medicines unless medicinal efficacy is claimed. | MHLW working-group summary, 2019-09-1339 |
| Anti-doping (WADA) | Not named on the 2026 Prohibited List. Section S0 covers pharmacological substances without current approval for human therapeutic use; we located no WADA ruling on whether it applies to NMN. “Not named” is not the same as permitted; the S0 reading is not a WADA statement about NMN. | WADA 2026 Prohibited List, in force 2026-01-0140 |
Regulatory status of NMN by jurisdiction, primary sources consulted 2026-10-17. Informational, not legal advice.
Three points are easy to miss. A novel-food authorisation attaches to a dossier, not to the molecule: if adopted as drafted, the EU entry covers one company’s synthetic β-NMN, with exclusivity for five years. An EFSA opinion is advice, not authorisation; the gap between May and September 2026 was the Commission and Member State procedure. And none of these food-law decisions concerns NMN supplied as a research-use-only reference material, which is not a food and must not be labelled or described as one.
How stable is NMN as a solid and in solution?
Stability data for NMN come from a kinetic study in solution, a forced-degradation study, cell-culture work and regulatory dossier data for the dry solid. They agree on direction and differ on magnitude.
| Source | Condition tested | Result |
|---|---|---|
| EFSA opinion, applicant data31 | Dry crystalline solid, sealed; 5 batches at 40 °C / 75% relative humidity for 6 months; 3 batches at 25 °C / 60% RH for 24 months | Identity, purity, water content and microbiology unchanged; proposed shelf life 24 months at room temperature in sealed containers; water specification ≤1.0% (batches 0.15–0.33%) |
| Xiang et al. 202341 | Aqueous solution, validated HPLC; temperature, pH, pepsin and trypsin | Apparent first-order degradation; at room temperature, 10% loss at 95.6 h and half-life 860 h; faster at high temperature and at strongly acidic or alkaline pH; little effect of pepsin or trypsin |
| Mills et al. 20164 | Solution in drinking water, room temperature, HPLC | 93–99% intact after 7–10 days |
| Zhou et al. 202442 | Forced degradation: acid, base, oxidation, light, heat | Significant degradation under basic and thermal stress |
| Kulikova et al. 201943 | Cell-culture medium with and without fetal bovine serum, HEK293 cells | With serum, NMN was degraded to NR even without cells; in serum-free medium NMN was relatively stable but partly converted to NR |
Published and regulatory stability data for NMN. Laboratory characterisation only.
The dry, sealed solid is the stable form: the only long-term data, from a regulatory dossier, show no change over 24 months at 25 °C and 60% RH. In solution NMN hydrolyses, and the two published room-temperature measurements differ roughly twofold (10% loss in about four days versus at most 7% in seven to ten days), most likely because of pH and matrix; neither reports conditions that would let the other be reproduced exactly. In cell work, serum in the medium converts NMN to NR before it reaches the cells, so an “NMN” condition in serum-containing medium is partly an NR condition.43 Conservative laboratory practice for reference materials (sealed, dry, cold, protected from light, solutions prepared fresh, single-use aliquots, vials brought to room temperature before opening) sits within these data.
One widely repeated claim lacks a primary source: we located no peer-reviewed measurement of NMN hygroscopicity, such as a dynamic vapour-sorption isotherm, in PubMed. The evidence that moisture matters is indirect: hydrolysis in solution and the water limits in dossier specifications.
Identity is a separate question. NMN exists as α and β anomers; β-NMN is the biological precursor. An isomer-specific LC-MS/MS method applied to eight commercial supplements found substantial variation in anomer composition, including undeclared or inaccurately labelled ingredients.44 A 2024 test of NMN and urolithin A supplements found active-ingredient content deviating from the label by +28.6% to −100%.45 A 2025 method for cosmetics found no NMN in some products that claimed it.46 Measuring NMN in blood or tissue has its own difficulty: endogenous levels are low, NMN is converted quickly during sample handling, and matrix effects distort LC-MS/MS signals. A 2024 method addressed this with two isotope-labelled NMN standards, one to correct matrix effects and one to trace losses during processing.47 Published NMN concentrations in biological samples are therefore comparable only when the methods are.
What is NMN, chemically?
| Name | β-Nicotinamide mononucleotide (β-NMN); nicotinamide ribonucleotide |
| PubChem CID | 1418048 |
| CAS | 1094-61-7 |
| Formula / molecular weight | C11H15N2O8P / 334.22 g/mol |
| InChIKey | DAYLJWODMCOQEW-TURQNECASA-N |
| Structure | Nicotinamide joined to ribose 5′-phosphate by a β-N-glycosidic bond; zwitterion at neutral pH |
| Synonyms used in PubMed | nicotinamide mononucleotide (1,538 title/abstract records), NMN, β-NMN, nicotinamide ribotide, nicotinamide ribonucleotide, MIB-626 (a pharmaceutical microcrystalline formulation) |
| Synonyms that mislead | “Alpha9” and other supplier trade names; “NMN” alone (also normetanephrine, N-methylnicotinamide) |
| Position in metabolism | Product of NAMPT from nicotinamide; converted to NAD+ by NMNAT1–3 |
Identity data from PubChem CID 14180 and the EFSA opinion; PubMed counts from the census query, 2026-10-17.
What is still not known?
- How NMN enters cells. The Imai group reported a dedicated transporter, Slc12a8;49 Schmidt and Brenner argued the data did not establish it.50 The 2026 human comparison suggests that gut microbial conversion to nicotinic acid explains much of the systemic NAD+ rise.25 Which route dominates in humans is unresolved.
- Whether the NAD+ rise does anything clinically. No human study has linked an NMN-induced change in blood NAD+ to a pre-specified clinical outcome with adequate power.
- What the unpublished trials found. Eleven finished registered trials, 620 participants enrolled, had no PubMed article at the cut-off; nine posted nothing.
- Long-term human safety. The longest human exposure is 24 weeks. A 2024 mouse preprint reported markers of kidney inflammation and higher circulating uraemic toxins in aged, but not young, mice given NMN.51
- Tissue NAD+ in humans. Most studies measure whole blood, plasma or PBMC. Brain NAD+ has been measured in one 12-person pharmacokinetic study.24
- Solution stability and hygroscopicity. Room-temperature solution estimates differ about twofold; no peer-reviewed sorption data exist for the solid.
How was this census built?
Identity and synonyms. PubChem CID 14180, 99 synonyms retrieved 2026-10-17. Each candidate synonym was counted in PubMed; “Alpha9” (951 records) and “nicotinamide nucleotide” (1,011, mostly NAD(P) and transhydrogenase) were rejected as ambiguous; “fosribnicotinamide” returned no records.
PubMed query (run 2026-10-17, 2,545 records): ("nicotinamide mononucleotide"[tiab] OR "Nicotinamide Mononucleotide"[mh] OR "beta-nicotinamide mononucleotide"[tiab] OR "beta-NMN"[tiab] OR "nicotinamide ribotide"[tiab] OR "nicotinamide ribonucleotide"[tiab] OR "MIB-626"[tiab] OR "fosribnicotinamide"[tiab] OR NMN[tiab]). All records were downloaded with NCBI E-utilities (efetch, XML).
Classification. Each record was classified from title, abstract, MeSH and publication type by deterministic rules: relevance (about NMN or another meaning of “NMN”), role (NMN given as a tested agent, NAD+ pathway biology, chemistry/production, review, comment) and model (in vitro, animal, human). Enzyme names containing the phrase “nicotinamide mononucleotide” were masked before role assignment. In version 0.9 every record previously labelled as an intervention (466) was reviewed by hand by title, and 125 labels were corrected; human intervention studies were identified by a targeted search and curated from abstracts and full texts, including funding and conflict-of-interest sections.
Blind double coding. A second coder, an independent model instance with the written codebook and no access to the first coder’s labels, classified a random 15% sample (382 records, seed 20261017). Against the first-pass rules, agreement on “NMN given as a tested agent versus not” was 88.2% (Cohen’s κ 0.65). The disagreements showed that the rules missed NMN used as a rescue, comparator or positive control in papers about other subjects. We added a sentence-level rule for those uses and reviewed the remaining edge cases by hand; agreement then rose to 95.0% (κ 0.87). Because the rules were revised after seeing this sample, the second figure is not an independent estimate; the first is the conservative one. Agreement on relevance was 80.1% (κ 0.57), lower because the second coder treated passing mentions of NMN inside NAD+ biology as not about NMN; on model, among records both coders called interventions, 85.6% (κ 0.71), with most disagreement over papers that use both cells and animals. A hand check of 40 records newly captured by the sentence rule found 32 correct, so the count of 626 may include roughly 40 false positives.
Full texts read. For the human layer, 21 of the 25 primary reports were read in full: 17 from PubMed Central, 2 from J-STAGE and 2 supplied as full texts (Yamane 2023, Pencina 2023 in J Clin Endocrinol Metab). Four were assessed from the abstract and registry only: Pencina 2023 in J Gerontol A, Akasaka 2023, Morifuji 2024 and Li 2026. For stability, Xiang 2023 and Zhou 2024 were assessed from their abstracts; the file supplied as Zhou 2024 was a different article and was not used.
Publication-type filters are unreliable here. The query combined with PubMed’s clinical-trial publication types returns 37 records; 16 are NMN intervention studies, and it misses 9 of the 25.
Registries. ClinicalTrials.gov API v2, queried 2026-10-17 with intervention and free-text searches for nicotinamide mononucleotide, β-NMN, MIB-626 and NMN; 57 records retrieved, 37 interventional with an NMN arm (NR-only, niacin, NMNH and unrelated studies excluded). Results articles were searched in PubMed by registration number and by the registrations cited in published trials. jRCT records were read individually where found; no rate was computed for jRCT, UMIN or ChiCTR.
Limitations. PubMed only (no Embase, CNKI or journals indexed only in J-STAGE); rule-based roles carry the error measured above; funding categories rely on what papers declare; the risk-of-bias column is a simplified judgement by one reviewer.
Data and code. The classified census (2,545 records), every table on this page, the blind-coding sample and agreement, and a data dictionary are in dataset.json (CC BY 4.0). The scripts that reproduce every number and figure are published with this page in nmn-evidence-card-scripts-v1.0-rc.zip: fetch_pubmed.py, parse_pubmed.py, census.py, ctgov.py, analysis.py, agreement.py, figures.py and build_body.py.
How to cite this dossier
Condor Research Editorial. NMN (β-nicotinamide mononucleotide) Evidence Card: literature census, human studies, registry gap and regulatory status. Version 1.0-rc, data cut-off 2026-10-17. https://condorresearch.com/research/what-is-nmn/. Dataset: dataset.json, CC BY 4.0.
Changelog. 1.0-rc2 (2026-10-18): RUO review wording changes. 1.0-rc (2026-10-17): explicit definition of “primary comparison” and recount of published confidence intervals (1 of 16 controlled studies with a designated primary; 3 without a designated primary; 3 assessed from abstract only); Kim 2022 registration UMIN000038097 added from its Methods, risk-of-bias judgement revised and studies without a cited registration reduced to 4; Yoshino 2021 row rewritten (significant three-way interaction, P = 0.022, without a contrast estimate); Igarashi 2022 supplier allocation error and exclusion of 22 participants’ week-12 data added to attrition and risk of bias; “Key findings” box added. 0.95 (2026-10-17): header and card rebuilt on the curated human and registry layers, with the census shown as context and its κ visible; Yamane 2023 and Pencina 2023 (J Clin Endocrinol Metab) re-read in full text: Yamane registration (UMIN000047042), attrition and funding statement added; Pencina design, attrition, absence of a designated primary and nominal P values added, CI count corrected from 5 to 4; full-text count added to Methods; Zhou 2024 kept at abstract level because the supplied file was a different article. 0.9 (2026-10-17): first public version. Intervention records reclassified by hand (466 reviewed, 125 corrected) and classification audited by blind double coding; primary-endpoint “success rate” replaced by a table of between-group results; registry gap reported as “no article located in PubMed at the cut-off”, separating articles, registry results and time since completion; EU authorisation details checked against the draft annex; 2026 GRADE review added; declaration of interest added.
References
- Yang W et al. Nutrients. 2026. PMID: 42514320 · doi: 10.3390/nu18142251
- Kane AE et al. bioRxiv. 2024. Preprint, not peer reviewed. PMID: 38979132 · doi: 10.1101/2024.06.21.599604
- Weiss B et al. Drug Des Devel Ther. 2026. PMID: 42011226 · doi: 10.2147/DDDT.S594895
- Mills KF et al. Cell Metab. 2016. PMID: 28068222 · doi: 10.1016/j.cmet.2016.09.013
- Irie J et al. Endocr J. 2020. PMID: 31685720 · doi: 10.1507/endocrj.EJ19-0313
- Liao B et al. J Int Soc Sports Nutr. 2021. PMID: 34238308 · doi: 10.1186/s12970-021-00442-4
- Yoshino M et al. Science. 2021. PMID: 33888596 · doi: 10.1126/science.abe9985
- Fukamizu Y et al. Sci Rep. 2022. PMID: 36002548 · doi: 10.1038/s41598-022-18272-y
- Huang H Front Aging. 2022. PMID: 35821806 · doi: 10.3389/fragi.2022.851698
- Igarashi M et al. NPJ Aging. 2022. PMID: 35927255 · doi: 10.1038/s41514-022-00084-z
- Kim M et al. Nutrients. 2022. PMID: 35215405 · doi: 10.3390/nu14040755
- Kimura S et al. Cureus. 2022. PMID: 36225528 · doi: 10.7759/cureus.28812
- Okabe K et al. Front Nutr. 2022. PMID: 35479740 · doi: 10.3389/fnut.2022.868640
- Akasaka H et al. Geriatr Gerontol Int. 2023. PMID: 36443648 · doi: 10.1111/ggi.14513
- Katayoshi T et al. Sci Rep. 2023. PMID: 36797393 · doi: 10.1038/s41598-023-29787-3
- Pencina KM et al. J Gerontol A Biol Sci Med Sci. 2023. PMID: 35182418 · doi: 10.1093/gerona/glac049
- Pencina KM et al. J Clin Endocrinol Metab. 2023. PMID: 36740954 · doi: 10.1210/clinem/dgad027
- Qiu Y et al. Signal Transduct Target Ther. 2023. PMID: 37718359 · doi: 10.1038/s41392-023-01577-3
- Yamane T et al. Clin Nutr ESPEN. 2023. PMID: 37344088 · doi: 10.1016/j.clnesp.2023.04.031
- Yi L et al. Geroscience. 2023. PMID: 36482258 · doi: 10.1007/s11357-022-00705-1
- Morifuji M et al. Geroscience. 2024. PMID: 38789831 · doi: 10.1007/s11357-024-01204-1
- Yamaguchi S et al. Endocr J. 2024. PMID: 38191197 · doi: 10.1507/endocrj.EJ23-0431
- Pencina KM et al. FASEB Bioadv. 2025. PMID: 40746868 · doi: 10.1096/fba.2025-00014
- Berven H et al. iScience. 2026. PMID: 41858901 · doi: 10.1016/j.isci.2026.114764
- Christen S et al. Nat Metab. 2026. PMID: 41540253 · doi: 10.1038/s42255-025-01421-8
- Li H et al. Nat Med. 2026. PMID: 42056497 · doi: 10.1038/s41591-026-04366-x
- Wakabayashi J et al. Sci Rep. 2026. PMID: 42304075 · doi: 10.1038/s41598-026-57552-9
- Yang DL et al. J Int Soc Sports Nutr. 2026. PMID: 41705654 · doi: 10.1080/15502783.2026.2632284
- Zhao C et al. Sci Rep. 2026. PMID: 41651893 · doi: 10.1038/s41598-025-34191-0
- Prokopidis K et al. J Cachexia Sarcopenia Muscle. 2025. PMID: 40275690 · doi: 10.1002/jcsm.13799
- EFSA NDA Panel EFSA J. 2026. PMID: 42125559 · doi: 10.2903/j.efsa.2026.10007
- ClinicalTrials.gov. NCT04571008, Effect of NMN Supplementation on Organ System Biology (Washington University School of Medicine); results first posted 11 March 2026. Accessed 2026-10-17. https://clinicaltrials.gov/study/NCT04571008
- European Commission. Consultation request for the determination of the novel food status of nicotinamide mononucleotide (Czech Republic). Published 11 October 2022. Accessed 2026-10-17. https://food.ec.europa.eu/system/files/2022-10/novel-food_consult-status_nmn-cz.pdf
- Regulation (EU) 2015/2283 of the European Parliament and of the Council on novel foods. Accessed 2026-10-17. https://eur-lex.europa.eu/legal-content/EN/TXT/?uri=CELEX:32015R2283
- European Commission, Comitology Register. D118035/02, draft Commission Implementing Regulation authorising the placing on the market of beta-nicotinamide mononucleotide (β-NMN) as a novel food; PAFF Committee positive opinion 24 September 2026. Accessed 2026-10-17. https://ec.europa.eu/transparency/comitology-register/screen/documents/118035/2/consult?lang=en
- European Commission. Novel food: decisions terminating the procedure (incl. C(2022) 1900 and C(2026) 6813 on nicotinamide mononucleotide). Accessed 2026-10-17. https://food.ec.europa.eu/food-safety/novel-food/decisions-terminating-procedure_en
- Food Standards Agency. Register of regulated product applications, RP-2116: β-Nicotinamide Mononucleotide (Effepharm (Shanghai) Ltd.), status in progress. Accessed 2026-10-17. https://data.food.gov.uk/regulated-product-applications/products-list/RP-2116
- US Food and Drug Administration. Response letter to the Natural Products Association and Alliance for Natural Health USA, docket FDA-2023-P-0872, 29 September 2025. Accessed 2026-10-17. https://www.regulations.gov/document/FDA-2023-P-0872-2754
- Ministry of Health, Labour and Welfare (Japan). Summary of the 2nd FY2019 working group on ingredients of pharmaceuticals, 13 September 2019. Accessed 2026-10-17. https://www.mhlw.go.jp/stf/newpage_07867.html
- World Anti-Doping Agency. International Standard Prohibited List 2026, in force 1 January 2026. Accessed 2026-10-17. https://www.wada-ama.org/sites/default/files/2025-09/2026list_en_final_clean_september_2025.pdf
- Xiang DH et al. Zhongguo Zhong Yao Za Zhi. 2023. PMID: 38212023 · doi: 10.19540/j.cnki.cjcmm.20230905.301
- Zhou H et al. J Chromatogr Sci. 2024. PMID: 36617938 · doi: 10.1093/chromsci/bmac107
- Kulikova V et al. Metabolites. 2019. PMID: 31795381 · doi: 10.3390/metabo9120293
- Hoei CS et al. Anal Chim Acta. 2026. PMID: 41545110 · doi: 10.1016/j.aca.2025.345027
- Sandalova E et al. Geroscience. 2024. PMID: 38935229 · doi: 10.1007/s11357-024-01257-2
- Lan T et al. J AOAC Int. 2025. PMID: 40193406 · doi: 10.1093/jaoacint/qsaf017
- Unno J et al. NPJ Aging. 2024. PMID: 38167419 · doi: 10.1038/s41514-023-00133-1
- PubChem. Compound summary CID 14180, nicotinamide mononucleotide. Accessed 2026-10-17. https://pubchem.ncbi.nlm.nih.gov/compound/14180
- Grozio A et al. Nat Metab. 2019. PMID: 31131364 · doi: 10.1038/s42255-018-0009-4
- Schmidt MS et al. Nat Metab. 2019. PMID: 32694648 · doi: 10.1038/s42255-019-0085-0
- Saleh TA et al. bioRxiv. 2024. Preprint, not peer reviewed. PMID: 38645109 · doi: 10.1101/2024.04.09.588624
Research Use Only. This page summarises published literature, public registries and regulatory documents. Condor Research supplies NMN strictly as a research-use-only reference material for in vitro and laboratory work. It is not a medicine, food or supplement, not intended for human or veterinary use, and nothing on this page is a recommendation to use any compound. Related: NMN research material · What is NAD+? · Longevity research compounds.
Does NMN raise NAD+ levels in humans?
In most studies that measured it. Of 25 human intervention studies published to October 2026, 17 measured NAD+ in blood and 15 reported an increase. In a 2026 randomised comparison the difference from placebo after 14 days was 43.1 µM (95% CI 32.7 to 53.4).
Has NMN been shown to slow ageing or improve health in people?
No. Of 16 controlled human studies with a designated primary endpoint, one publishes a confidence interval for the difference from control; most are small and short, and the longest lasted 24 weeks. A 2026 systematic review with GRADE found no broad metabolic benefit.
Is NMN legal in the EU?
As a food it is a novel food not yet on the Union list. EFSA judged one applicant's β-NMN safe in May 2026, and a draft regulation listing it, with five years of data protection for that applicant, received a positive committee vote on 24 September 2026; it was not published in the Official Journal by 17 October 2026.
What did the FDA decide about NMN in 2025?
On 29 September 2025 FDA concluded that NMN is not excluded from the US dietary-supplement definition under the race-to-market clause, reversing its 2022 view. The letter addresses that clause only; it is not an approval of any product and does not decide safety or other legal requirements.
Who funded the human NMN trials?
Mostly industry. Of 25 human studies, 12 were funded or sponsored by a company and 8 more had declared ties to NMN manufacturers, such as donated product or company employees among the authors. Five declared no industry involvement.
How stable is NMN?
The dry, sealed solid is stable: regulatory dossier data show no change over 24 months at 25 °C and 60% relative humidity. In water NMN hydrolyses; one kinetic study measured 10% loss after about 96 hours at room temperature, faster at high temperature or extreme pH.